

Understanding anatomy, indications, and clinical guidelines is not enough. Procedures also require coordinated movements, instrument control, image interpretation, equipment setup, workflow discipline, and risk management.
Many of these skills cannot be learned through observation alone. Clinical opportunities are limited, cases vary, and complex or high-risk events may occur too infrequently for sufficient practice. Medical simulation models help close this gap by letting learners rehearse defined tasks, procedures, and team workflows without relying solely on patient encounters.
"The central selection principle: The best simulator is not necessarily the largest, most technologically complex, or most realistic in every respect. It is the one that reproduces the elements that matter for the intended learning objective."
What Are Medical Simulation Models?
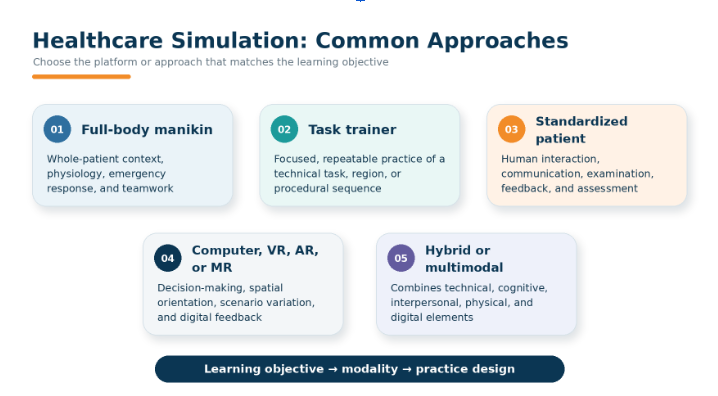
The Healthcare Simulation Dictionary, Third Edition, developed by the Society for Simulation in Healthcare (SSH), defines a simulator as a setting, device, computer program, or system that performs simulation. A simulation modality is the approach used in an activity and should reflect its complexity and learning objectives.
Healthcare simulation is not a single equipment category, and the dictionary is not a formal taxonomy. Standardized patients, for example, are trained people who portray patients; they are an important approach, but not a type of physical simulator.
In practice, healthcare simulation may be delivered through manikin-based scenarios, task trainers and procedural simulators, standardized or simulated patients, computer-based environments, virtual reality (VR), augmented reality (AR), mixed reality (MR), and hybrid or multimodal experiences. This article focuses primarily on physical and hybrid simulators designed for hands-on procedural skills training.
| Approach | Best suited to | Main strengths | Typical limitations |
| Full-body manikin-based simulation | Patient assessment, emergency response, physiology, teamwork, and integrated scenarios | Supports whole-patient context, monitoring, communication, and team roles | May provide limited detail or tissue response for a specific invasive procedure |
| Task trainer or procedural simulator | Repeated practice of a defined technical task, anatomical region, or procedural sequence | Focused, repeatable, and efficient for psychomotor skill development | May provide less whole-patient context unless combined with another modality |
| Standardized or simulated patient | History taking, communication, physical examination, professionalism, and assessment | Human interaction, emotional realism, and structured feedback | Invasive procedures require a substitute body part, model, or hybrid setup |
| Computer-based, VR, AR, or MR simulation | Decision-making, anatomy, spatial orientation, procedural rehearsal, and scenario variation | Scalable content, repeatable scenarios, and potential performance tracking | Haptics, real-device interaction, and physical setup may be limited |
| Hybrid or multimodal simulation | Experiences that combine technical, cognitive, and interpersonal skills | Can connect a task trainer or physical model with a simulated patient, digital layer, or team scenario | Requires more design, facilitation, integration, and operational planning |
Educators should select approaches by the job to be learned; many programs benefit from a deliberate combination of modalities.
Task Trainers for Focused Clinical Skills Practice
Task trainers represent a specific body part, anatomical region, or procedural interface rather than an entire patient. They support deliberate, repeatable practice of defined skills or sequences, helping learners build psychomotor coordination, recognize anatomy, handle instruments, and receive feedback without exposing patients to training-related risk.
The category is much broader than needle insertion or vascular access. A task trainer may be a head for airway management, an arm with a simulated vascular system, a multilayer suturing pad, a torso for chest tube placement, a spine model for lumbar puncture or epidural access, or a pelvis for catheterization and examination.
Table 2. Representative task-trainer applications across clinical skills
| Skill area | Procedures or skills | Representative trainer formats |
|---|---|---|
| Airway management | Bag-mask ventilation, endotracheal intubation, supraglottic airway insertion, and cricothyrotomy | Airway or intubation head trainers with relevant oral, pharyngeal, laryngeal, tracheal, and esophageal anatomy |
| Vascular access and injections | Venipuncture, intravenous access, arterial cannulation, intramuscular injection, and subcutaneous injection | IV arms with simulated vessels and fluid, vascular access models, and layered injection pads |
| Wound care and suturing | Suturing, knot tying, suture removal, debridement, and wound assessment | Multilayer suturing pads and wound models with varied incision or defect patterns |
| Advanced access and critical procedures | Central venous access, lumbar puncture, epidural access, chest tube insertion, and intraosseous access | Torso, spinal, thoracic, and ultrasound-compatible vascular trainers; advanced models may reproduce cerebrospinal-fluid return or loss-of-resistance feedback as appropriate to the procedure |
| Examinations and routine catheterization | Urinary catheterization, pelvic examination, prostate examination, and breast palpation | Pelvic trainers, examination models, and palpation models with replaceable anatomy or findings |
Any skill requiring hand-eye coordination, anatomical recognition, instrument handling, and a defined sequence may benefit from a task trainer that balances meaningful practice with practicality for repeated use.
Why Procedure-Specific Simulation Is Increasingly Important
The case for procedure-specific simulation is driven less by condition prevalence than by procedural demands and risks. Common pressures across minimally invasive, surgical, emergency, and interventional care include:
- Technical complexity: A procedure may require several coordinated actions rather than one isolated movement.
- Limited supervised opportunities: Learners may not encounter enough suitable cases to practice every step repeatedly.
- Concurrent information streams: The operator may need to interpret imaging, manipulate an instrument, monitor device behavior, and maintain sterility at the same time.
- New devices and techniques: Clinical teams and medical-device users need a repeatable environment in which to learn unfamiliar equipment before use in patients.
- Rare but consequential events: Complications and equipment failures may be infrequent, yet teams must be ready to recognize and manage them.
- Standardization and assessment: Educators need comparable conditions when teaching, evaluating, or certifying learners.
These pressures change the design brief: anatomical appearance alone is insufficient if the model does not support the instruments, imaging, pathway, and risks that define the task.
How Procedure-Specific Simulators Support Different Technical Skills
Because clinical specialties overlap, examples are clearer when organized by the dominant technical task rather than disease, specialty, or imaging modality. The following is a practical framework, not a formal classification.
Table 3. Practical skill families for procedure-specific simulation
| Technical skill family | Representative applications | What the simulator may need to reproduce |
|---|---|---|
| Access and placement | Airway placement, peripheral or central vascular access, urinary catheterization, chest or drainage catheter placement, and large-bore vascular cannulation for extracorporeal or mechanical circulatory support (MCS) | Entry anatomy, target depth, puncture or insertion feedback, trajectory, device position, and confirmation cues |
| Examination, imaging, and targeting | Palpation, ultrasound scanning, aspiration, biopsy, lesion localization, and marker placement | Detectable findings, target and surrounding anatomy, imaging appearance, probe or instrument coordination, and safe trajectories |
| Navigation and device deployment | Endoscopy, guidewire and catheter navigation, angioplasty, stenting, embolization, valve delivery, and occluder placement | Anatomical pathways, access routes, visualization, device movement, deployment space, and compatibility with intended equipment |
| Tissue treatment and repair | Suturing, knot tying, dissection, anastomosis, excision, hemostasis, and ablation | Tissue layers, handling and resistance, target boundaries, energy-device interaction, repair sequence, and treatment endpoint cues |
| Integrated workflow and complication management | Complete procedural sequences, equipment connection, emergency conversion, complication recognition, troubleshooting, and team coordination | Workflow dependencies, physiological or circuit behavior, device interfaces, role coordination, abnormal events, and opportunities for debriefing |
This structure avoids giving any application disproportionate weight. For example, ECMO cannulation belongs within access and placement, while circuit connection and failure management belong within integrated workflow and complication management. Likewise, interventional oncology extends beyond biopsy and ablation to lesion localization or marker placement and embolization.
The distinction is also visible in current training requirements. For example, the Extracorporeal Life Support Organization’s adult certification pathway requires a high-fidelity simulation lab that covers drainage insufficiency, air embolism, pump failure, membrane-lung failure, and gas failure. These are integrated troubleshooting and response scenarios, not simply cannulation tasks.
Image guidance is a cross-cutting requirement
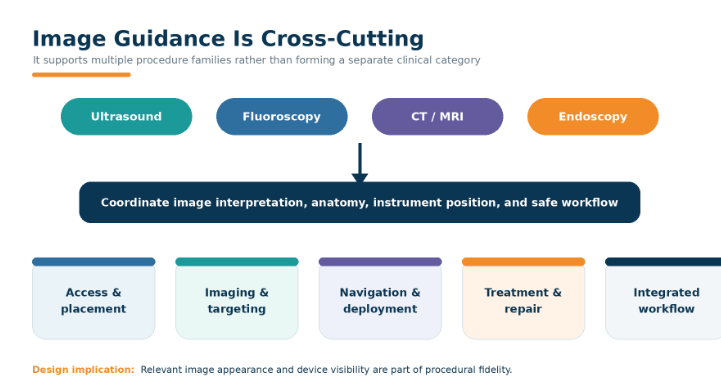
Image guidance is not a separate clinical category but a cross-cutting technical requirement across several skill families. It may involve ultrasound, fluoroscopy, CT, MRI, endoscopy, or direct visualization.
For ultrasound-guided procedural training, learners may need to coordinate the probe and instrument, maintain the target in view, understand orientation, recognize artifacts, control the needle or device trajectory, and protect nearby structures. The simulator must therefore do more than contain approximate anatomy: it needs relevant image appearance, instrument visibility, spatial relationships, and compatibility with the intended clinical equipment.
This makes image-guided procedural training, particularly ultrasound-guided practice, more precise here than the broader term POCUS, which also covers diagnostic and assessment applications.
Three Questions for Purposeful Procedural Simulation Design
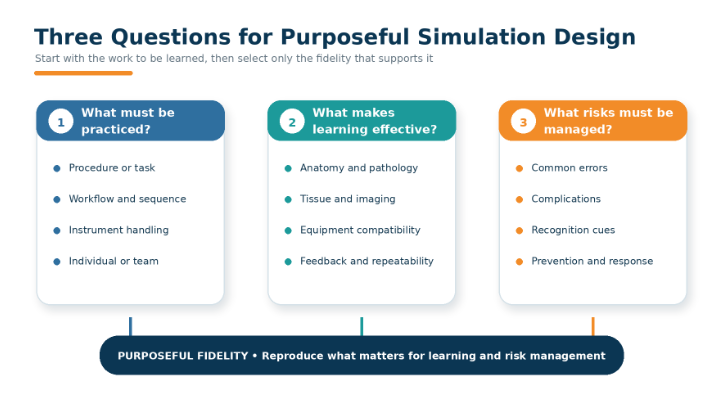
At SurgMate, simulator design begins with three questions. Together, they prevent the design process from becoming a search for maximum realism without a clear educational purpose.
1. What procedures, workflows, and skills must learners practice?
The first question defines the scope of the experience. Is the goal to practice one component, a complete procedure, or a team-based workflow? Does the learner need to master instrument handling, a sequence of steps, equipment setup, decision points, or communication? Is the platform intended for novice familiarization, proficiency development, structured assessment, or device training?
This decision determines whether a focused task trainer is sufficient or whether the simulator must support multiple connected stages.
2. Which critical elements determine whether learning will be effective?
Only the features that influence performance should drive fidelity. Depending on the application, these may include anatomical and pathological relationships, tissue feel, imaging appearance, device visibility, real-equipment compatibility, circulation or pressure, feedback, reproducibility, and the ability to reset the model between learners.
For example, an ultrasound-guided biopsy platform may require a recognizable lesion, a safe access window, realistic device visibility, and replaceable puncture components. A catheter-based intervention may depend more on the geometry of the access route, friction, circulation, device tracking, and deployment space.
3. Which common errors, risks, or complications must learners recognize and avoid?
Training design should identify not only the ideal sequence, but also the errors that matter: incorrect trajectory, damage to adjacent structures, malposition, loss of access, device misuse, air entry, bleeding, circuit problems, or a failure to recognize an abnormal response.
Not every risk must be physically reproduced. Some are best represented by anatomy or tissue behavior; others can be introduced through scenario cues, digital overlays, facilitator input, physiological changes, or hybrid simulation. The design question is how learners will practice prevention, recognition, and response.
Match Fidelity to the Learning Goal
Fidelity is often discussed as a single scale from low to high. In practice, a simulator can be highly realistic in one dimension and intentionally simple in another. Visual appearance, anatomical accuracy, tissue response, imaging, physiology, device interaction, and environmental context are separate design choices.
Basic models and accessible materials can be appropriate for early skill acquisition. A suturing pad may be enough to practice needle angles and knot mechanics. A simple vessel phantom may support initial probe-hand coordination and needle visualization. These options can be low cost, portable, and easy to replace.
Their limitations become important when the learning objective requires consistent anatomy, defined lesion locations, realistic pathways, clinical imaging, physiological behavior, or use of the complete device workflow.
Ex vivo animal organs and tissues remain common in procedural training because they can be relatively inexpensive and provide useful tactile practice. They also create practical requirements for sourcing, preservation, hygiene, storage, and biological-waste disposal, while their use may raise ethical or cultural acceptability concerns. When a simulator can meet the objective without animal-derived material, it can avoid many of these burdens while providing more standardized anatomy, repeatability, and easier deployment. This does not make synthetic models automatically superior: their material response and clinical relevance must still be matched to the target skill.
Advanced features are valuable only when they serve the intended task. The most useful question is:
"Does this simulator reproduce the anatomy, imaging, equipment interaction, procedural steps, and risk cues required by the learning objective?"
This idea can be described as purposeful fidelity: reproduce what matters for learning and assessment, and avoid complexity that adds cost or maintenance without improving the training experience.
How to Select the Right Medical Simulation Model
Selection should start with an educational and operational brief, not a product catalog. The following checklist helps hospitals, medical schools, training organizations, and medical-device companies compare options consistently.
Table 4. A 10-point selection checklist for medical simulation models
| Selection factor | Questions to ask | Why it matters |
|---|---|---|
| Learning objective | What should the learner be able to perform, recognize, or decide after training? | Defines the simulator’s necessary functions and prevents irrelevant complexity |
| Procedure and workflow | Is the target one task, a full procedure, equipment setup, or a team response? | Determines the required scope and whether hybrid simulation is needed |
| Anatomy and pathology | Which structures, variants, lesions, or spatial relationships affect performance? | Ensures that practice reflects the intended access route and clinical challenge |
| Imaging and visualization | Must the model work with ultrasound, fluoroscopy, CT, MRI, endoscopy, or direct observation? | Image appearance and device visibility can be essential to successful practice |
| Instrument and device compatibility | Will learners use the intended needles, guidewires, catheters, cannulas, ablation devices, circuits, consoles, or monitoring equipment? | A realistic-looking model may still fail if it cannot support the actual tools |
| Physiology and feedback | Are circulation, pressure, fluid return, hemodynamics, resistance, alarms, or performance feedback required? | Adds dynamic information only where it affects the learning objective |
| Mobility and deployment | Will the simulator move between classrooms, hospitals, conferences, or customer sites? Can the intended team pack, carry, protect, and set it up efficiently? | Portability affects outreach training, medical-device demonstrations, transport risk, and setup time |
| Repeatability and throughput | How quickly can the platform be set up, reset, cleaned, and used by the next learner? | Directly affects course capacity, consistency, and facilitator workload |
| Consumables and total cost | Which parts wear out, how often are they replaced, and what storage and maintenance are required? | Purchase price alone does not represent the operating cost of repeated training |
| Standard or customized solution | Does an existing platform reproduce the anatomy, device, procedure, and workflow, or is specialized development required? | Prevents a training program from being forced around an unsuitable model |
Standard platform or customized development?
A standard platform is usually the most efficient choice when its anatomy, functions, and equipment interfaces already match the intended application. It reduces development time and can be easier to procure, support, and scale.
Customized development becomes more appropriate when the training involves unusual or patient-specific anatomy, a new medical device, a specialized lesion or pathology, a proprietary workflow, a device demonstration, usability evaluation, R&D testing, or a procedure not supported by available models. In that situation, the simulator should be designed around the learning objective, anatomy, device, and workflow, rather than forcing users to adapt to an unrelated platform.
Modularity is valuable in either case. If frequently punctured vessels, tissue sections, targets, or lesions can be replaced independently, the main platform can remain in service while consumable cost and setup time are controlled.
The Future of Physical-Digital Procedural Simulation
Physical and digital simulation are increasingly complementary. Mixed reality can add anatomy labels or procedural cues to physical models, while sensors and software can support feedback, case variation, and performance review. AI may help generate scenarios or personalize feedback when supported by appropriate data and validation.
These capabilities should be added selectively. Every physical or digital feature should support a defined objective and address usability, privacy, safety, and validation.
SurgMate’s Focus on Procedure-Specific Simulation
At SurgMate, we develop realistic, modular simulation platforms for hands-on procedural training, with particular experience in cardiovascular and endovascular procedures, image-guided tumor interventions, and other minimally invasive applications. Across these areas, we pay particular attention to ultrasound-guided training, relevant anatomy, clinical-equipment compatibility, repeatability, and the procedural details that affect learning. Examples include the ECMO Cannulation and Endovascular Procedures Training Platform (EVAN), the NeoPeds Endovascular Procedures Training Platform (DORA), and organ-specific platforms for thyroid biopsy and ablation, breast examination, biopsy and ablation, and uterine fibroid biopsy and ablation.
When a standard platform does not match the intended anatomy, device, or workflow, SurgMate also provides contract design and manufacturing services (CDMS) for customized medical simulators, skills-training platforms, medical-device test benches, and demonstration kits. The same three design questions guide both standard products and customized development: what must be practiced, what determines effective learning, and which risks must be recognized or avoided.

Select Around the Procedure, Not Just the Model
Medical simulation models give educators and device teams more ways to build procedural competence outside clinical care, but also make selection more complex.
Start with the procedure: define the skill, workflow, anatomy, imaging, equipment, risk cues, training frequency, and replacement needs. Then select a task trainer, integrated physical simulator, computer-based, VR, AR, or MR environment, hybrid experience, or customized platform.
A simulator should not merely resemble clinical care. It should make the intended practice consistent and repeatable, and make learner performance easier to observe, assess, and improve.
Explore procedure-specific training platforms
Explore SurgMate medical simulation products for cardiovascular, interventional, and tumor-treatment applications.
Discuss a custom training or device application
Contact SurgMate to discuss a specialized procedure, medical-device demonstration, test bench, or customized simulation platform.